 Skip to content


What Happens During a Plantar Fasciitis Consultation and Assessment in Stratford-upon-Avon?
If you’ve been struggling with plantar fasciitis or persistent heel pain, you may be wondering what actually happens during an initial consultation — and whether it will be any different from the things you’ve already tried.
At Heel Your Pain in Stratford-upon-Avon, the initial consultation is a one-to-one £49 assessment with Stephen Grinnell MSc, Physical Rehabilitation Specialist.
The purpose is simple: to understand what is happening, what you have already tried, how your foot is behaving when you stand and walk, and what may need to change next.
During your consultation, we will look at:
- Your history — when the pain started, how it behaves, and what you have already tried.
- How you stand and walk — including the way you load the foot and move after rest.
- Relevant foot, ankle and lower-limb movement — to identify areas that may be contributing to the problem.
- Your footwear and daily activity — where these are relevant to your symptoms.
- What you want to get back to doing — whether that is walking, running, golf, work, holidays or simply getting through the day more comfortably.
By the end of the consultation, the aim is for you to leave with:
- a clearer understanding of your heel pain;
- an explanation of what we have found;
- a better idea of what may be contributing to the problem;
- and a clear recommendation for the most appropriate next step.
The consultation is not about giving you another random stretch or exercise.
It is about looking at the bigger picture — how you stand, walk, move and load the foot throughout the day — and then using that information to build a more individual approach to recovery.
Why this assessment matters
Many people who come to see me have already tried several different things.
They may have changed shoes, bought insoles, stretched, rested, rolled the foot, tried exercises, seen a physio or had other treatments.
Sometimes those things help temporarily.
But one of the questions I always want to understand is:
What is happening every time you stand up and every time you take a step?
Because those are movements you repeat hundreds or thousands of times every day.
That is why the Heel Your Pain assessment starts by understanding the way you move — before deciding what should happen next.
A Structured Medical History will be required and any obvious trigger event for the plantar fasciitis, like a fall, or a change in exercise like couch to 5KM.
Most cases of Plantar Fasciitis do not have an easily identifiable trigger event or trauma.
Physical Examination Techniques
The physical examination aims to confirm the clinical suspicion of plantar fasciitis, assess biomechanical contributors, and exclude alternative diagnoses. Key components include inspection, palpation, range of motion, strength testing, functional assessment, and special tests.
Inspection of feet
- Gait observation: walking gait, altered foot strike, or compensatory patterns.
- Posture and foot type: Flat feet, high arches, or abnormal pronation/supination.
- Swelling, erythema, or bruising: Uncommon in plantar fasciitis; may suggest alternative issues pathology.
- Footwear assessment: Wear patterns, support, and fit.
Hands On
- Maximal tenderness at the heel of foot at the plantar fascia insertion is highly suggestive.
- Plantar fascia: Pressure along its length for focal or diffuse tenderness.
- Fat pad, calcaneus, and arch: Assess for atrophy, masses, or bony abnormalities.
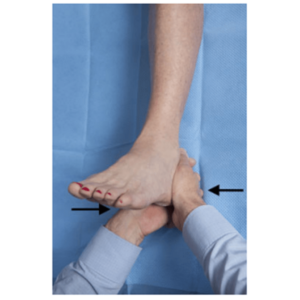
- Tinel’s sign: Pressure and movement over the tarsal nerve tunnel to assess for nerve irritation.
Range of Motion and Strength
- Ankle dorsiflexion: Limited range may contribute to plantar fascia strain.
- Midfoot motion: Assess for restriction or hypermobility.
- Big toe extension: Evaluate for pain or limitation.
- Muscle strength: Test calf, internal foot, and peroneal muscles.
Functional and Gait Assessment
- Heel raise test: Assess for pain or weakness.
- Single-leg stance and squat: Evaluate balance and functional capacity.
- Gait analysis: Identify overpronation, altered stride, or compensatory mechanisms.
Special Tests specific to plantar fasciitis
Windlass Test
The Windlass test is a key diagnostic manoeuvre:
- Non-weight-bearing: With the patient seated and knee flexed, the examiner dorsiflexes the great toe while stabilising the ankle. Reproduction of heel pain is a positive test.
- Weight-bearing: The patient stands with the toes over the edge of a step; the examiner dorsiflexes the great toe. Pain at the medial heel is a positive result.
A positive Windlass test has high specificity but variable sensitivity for plantar fasciitis.
Tinel’s Sign
Percussion over the posterior tibial nerve at the tarsal tunnel elicits tingling or pain in cases of tarsal tunnel syndrome, helping to differentiate from plantar fasciitis.
Squeeze Test
Compression of the calcaneus may reproduce pain in stress fracture or fat pad pathology.
Functional and Gait Assessment
Biomechanical factors play a significant role in plantar fasciitis. Gait analysis, either clinical or using advanced motion-capture technology, can identify:
- Reduced ankle dorsiflexion
- Excessive pronation or supination
- Altered step length or cadence
- Weakness in calf or hip muscles
- Low or high arches
Gait analysis informs targeted interventions, such as orthotics, footwear modification, or physiotherapy for specific issues.
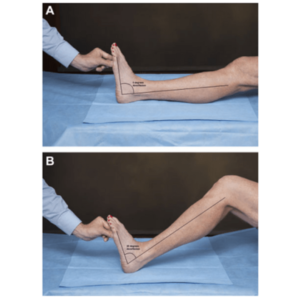
The problem with most gait analysis is that it focuses on a very specific area. For example Reduced ankle dorsiflexion or how high you can raise your foot, the minimum range of movement for an ankle is 90 degrees or what is described as Plantar Grade. Range of movement from plantar grade, 20 degrees past this point is good dorsiflexion pulling foot up and 50 degrees of plantar flexion pushing the foot down.
Why walking matters
Persistent plantar fasciitis can be influenced by several factors. One of the areas I pay particular attention to is how you stand, walk and load the foot throughout the day.
The assessment helps identify movement patterns and loading strategies that may be contributing to your symptoms, so we can build a more individual rehabilitation plan.
Visual Observation
- We’ll watch you walk naturally in a straight line.
- We may ask you to walk for a more extended period outside in shoes.
- If relevant, we might observe you running as well.
Biomechanical Assessment
- We analyse the movement of your feet, ankles, knees, hips, and lower back.
- We look for any asymmetries or irregularities in your gait.
Foot Strike Pattern
- We observe how your foot lands (heel, midfoot, or forefoot).
- We check for overpronation or supination.
Stride Length and Width
- We measure the length and width of your steps.
- Abnormalities here can indicate compensation for pain.
Timing and Rhythm
- We assess the timing of each phase of your gait cycle.
- Irregularities can point to specific areas of discomfort.
Muscle Activity
- We observe which muscles are active during different phases of your gait.
- This helps identify any muscle imbalances or weaknesses.
Joint Angles
- We analyse the angles of your joints during movement.
- This can reveal issues with flexibility or joint function.
Pressure Distribution
- Observation to see how weight is distributed across your feet.
- This helps identify areas of excessive pressure that could contribute to plantar fasciitis.
Video Analysis
- We might record your gait for a more detailed analysis.
- Slow-motion playback allows us to catch subtle irregularities.
Footwear Assessment
- We’ll examine your shoes for wear patterns.
- This can provide insights into your typical gait patterns.
Conclusions and Treatment Plan
At the end of the Assessment a summary of key findings and solutions are presented to you and a treatment plan is outlined and explained.
